The short answer
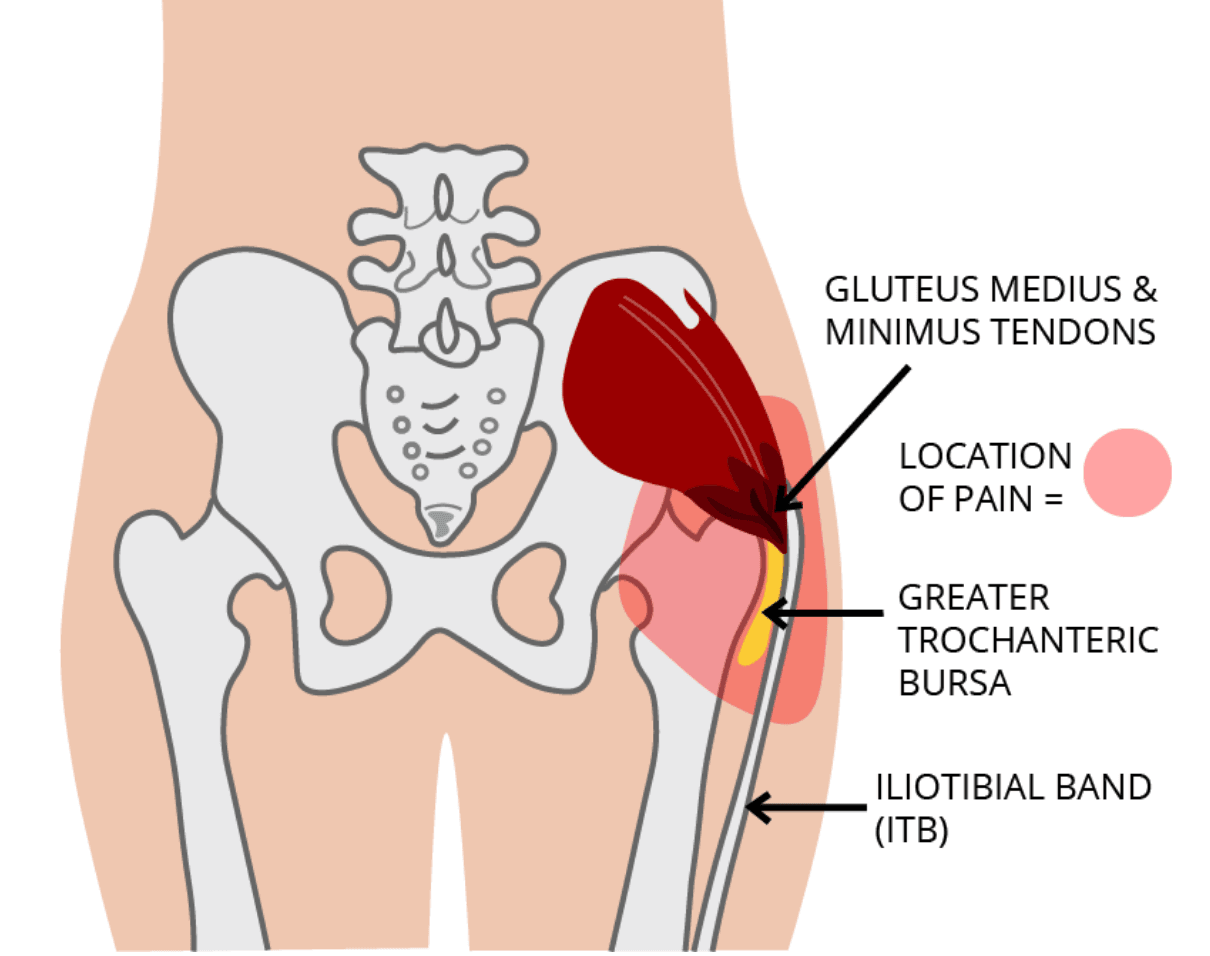
Gluteal tendinopathy is injury to the gluteus medius and minimus tendons where they attach to the greater trochanter on the side of the hip. Often misdiagnosed as bursitis, it causes outer-hip pain, tenderness, and weakness — worse when lying on that side. Treatment centers on gluteal strengthening, with cortisone or PRP for persistent cases.

Medically reviewed by Marc Gruner, DO, MBA, RMSK
Sports medicine physician, Mayo Clinic fellowship. Last reviewed June 2026
Overview
Gluteal tendinopathy involves injury — primarily to the gluteus minimus and medius tendons — where they attach to the greater trochanter on the outside of the hip. It is frequently misdiagnosed as trochanteric bursitis, but the underlying problem is tendon overuse and micro-damage. It causes pain on the side of the hip that is often worse when lying on that side.
Dr. Gruner emphasizes physical therapy to strengthen the gluteal muscles, with ultrasound to confirm the diagnosis. Cortisone into the trochanteric bursa or ultrasound-guided PRP can help persistent cases, and surgical repair is reserved for the rare tendon that fails to respond.
Common symptoms
- Pain on the side of the hip
- Pain worse when lying on that side
- Tenderness over the tendons
- Pain and weakness with strength testing
What to expect at your visit
- 1.
A focused conversation
Dr. Gruner reviews your history, prior imaging, and goals — what you want to get back to doing.
- 2.
Point-of-care ultrasound
When useful, a diagnostic musculoskeletal ultrasound evaluates the injury in real time, with no radiation.
- 3.
A clear, individualized plan
You leave understanding the diagnosis, the non-surgical options, and the expected timeline — in plain language.
Rehabilitation protocol
What to expect week by week after your procedure. Your plan is individualized; follow these alongside your physical therapist.
Hip (Gluteal Tendon) — Ultrasound-Guided Lipogems / PRP Protocol
Week 1
Protect the tendon
- No weight-bearing 4 days, then toe-touch; wean off crutches by end of week 1
- Gentle hip-flexion ROM from day 4, 4×/day
- Optional BFR from day 4
Week 2
Pain-free ROM
- Progress weight-bearing with crutches
- Begin isometrics, straight-leg raises, clamshells
- Core stability; pool once wound healed
Weeks 3–6
Build strength
- Progress hip-abductor strengthening
- May begin stationary bike
Weeks 6–12
Return to sport
- Sport-specific exercises; balance and higher-impact activity
- Soft-tissue work (no foam rolling until week 6)
Do not use NSAIDs (ibuprofen, Aleve, aspirin) for 4 weeks, and avoid ice for the first week — both blunt the healing response. Acetaminophen (Tylenol) is fine for discomfort. Care is tailored to you; use these guidelines with your physical therapist.
Clinical evidence
Selected peer-reviewed research supporting these approaches.
Frequently asked questions
- Is my outer hip pain bursitis or tendinopathy?
- What is often called 'hip bursitis' is frequently gluteal tendinopathy — a tendon problem rather than pure bursa inflammation. Ultrasound helps distinguish them, which matters because tendon problems respond best to targeted strengthening and, if needed, PRP.