The short answer
Golfer's elbow (medial epicondylitis) is injury to the common flexor tendon on the inside of the elbow, caused by repeated wrist flexion. It produces pain and stiffness over the inner elbow, pain down the arm, and trouble gripping. Treatment includes activity modification, bracing, and physical therapy, with ultrasound-guided PRP or Tenex for resistant cases.

Medically reviewed by Marc Gruner, DO, MBA, RMSK
Sports medicine physician, Mayo Clinic fellowship. Last reviewed June 2026
Overview
Golfer's elbow (medial epicondylitis) is a degenerative injury of the common flexor tendon where it attaches to the inside of the elbow. As with tennis elbow, it isn't limited to golfers — anyone who repeatedly flexes the wrist under load can develop it.
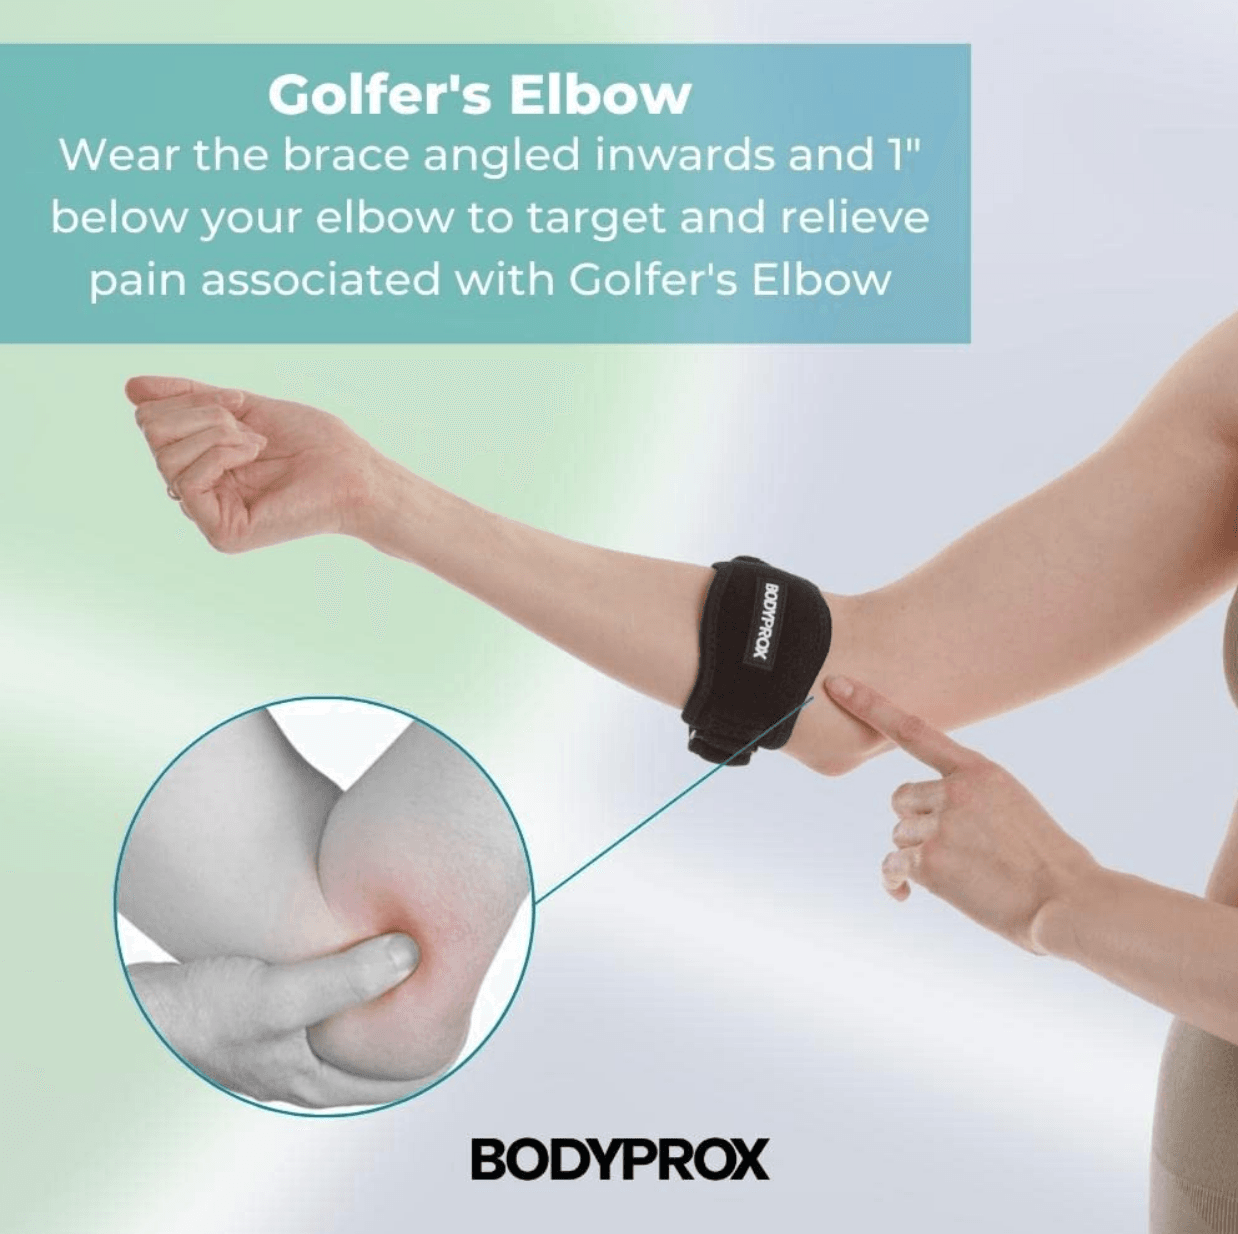
Care begins with activity modification, a brace positioned about an inch below the elbow, and physical therapy including massage, dry needling, and progressive strengthening over 4–6 weeks. For persistent pain, Dr. Gruner offers ultrasound-guided PRP or percutaneous tenotomy (Tenex).
Common symptoms
- Pain and stiffness over the inside of the elbow
- Pain radiating down the arm
- Difficulty grabbing objects
Videos from Dr. Gruner
Golfer's Elbow Symptoms and Treatment — Dr. Marc Gruner
Tennis Elbow vs. Golfer's Elbow — Dr. Marc Gruner Explains
What to expect at your visit
- 1.
A focused conversation
Dr. Gruner reviews your history, prior imaging, and goals — what you want to get back to doing.
- 2.
Point-of-care ultrasound
When useful, a diagnostic musculoskeletal ultrasound evaluates the injury in real time, with no radiation.
- 3.
A clear, individualized plan
You leave understanding the diagnosis, the non-surgical options, and the expected timeline — in plain language.
Rehabilitation protocol
What to expect week by week after your procedure. Your plan is individualized; follow these alongside your physical therapist.
Elbow — Ultrasound-Guided Tenotomy / PRP Protocol
Week 0–1
Protect, reduce pain and swelling
- Sling for 3 days; no driving in sling
- May lift up to 5 lbs; rest and elevate
- Begin gentle active ROM 4×/day on day 3
- Optional blood-flow-restriction (BFR) training 2×/week
Weeks 1–2
Restore full range of motion
- May lift up to 10 lbs
- Avoid repetitive elbow/hand activity and sustained gripping
- Regain full ROM 3–5×/day
Weeks 2–4
Begin strengthening
- May lift up to 20 lbs
- Begin isometric wrist/elbow strengthening
- Week 3: add light wrist flexion/extension weight (~2 lbs)
Weeks 4–6
Build strength and function
- Progress isotonic strengthening
- Integrated strengthening (chest press, rows, hammer curls)
- Begin eccentric training
Weeks 6+
Return to sport
- Continue strengthening
- Sport-specific and progressive loading exercises
Do not use NSAIDs (ibuprofen, Aleve, aspirin) for 4 weeks, and avoid ice for the first week — both blunt the healing response. Acetaminophen (Tylenol) is fine for discomfort. Care is tailored to you; use these guidelines with your physical therapist.
Frequently asked questions
- What is the difference between golfer's elbow and tennis elbow?
- Golfer's elbow affects the flexor tendon on the inside of the elbow (from wrist flexion), while tennis elbow affects the extensor tendon on the outside (from wrist extension). Both are overuse tendon injuries treated similarly.