The short answer
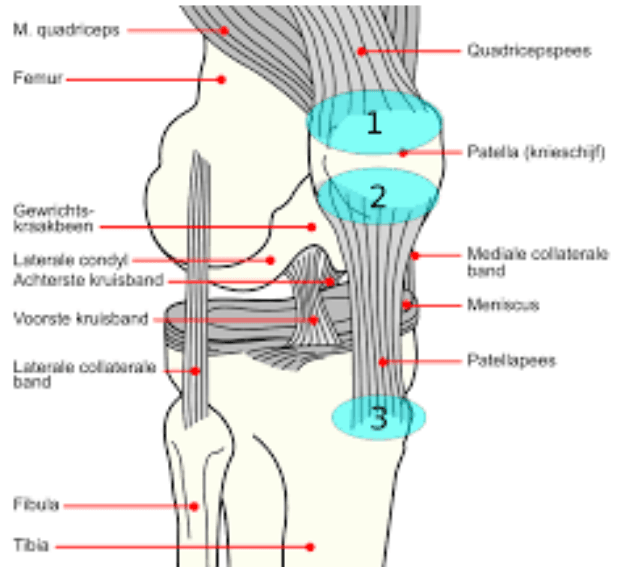
Quadriceps tendinopathy is micro-damage and overuse of the tendon above the kneecap that connects the patella to the quad muscles, most common after age 40. It causes pain above the kneecap with squatting and stairs. Because it is a tendon injury rather than inflammation, cortisone is avoided; treatment centers on loading, physical therapy, and PRP or Tenex.

Medically reviewed by Marc Gruner, DO, MBA, RMSK
Sports medicine physician, Mayo Clinic fellowship. Last reviewed June 2026
Overview
The quadriceps tendon sits just above the kneecap, connecting it to the quad muscles, and helps with jumping and cushioning landings. Quadriceps tendinopathy involves excessive stress and micro-damage to this tendon, typically affecting people over 40. Though historically called tendonitis, it is characterized by tendon injury, not inflammation.
Dr. Gruner treats it with activity modification (changing landing and squat mechanics, reducing jumping and stairs) and a physical therapy loading program. For persistent cases, ultrasound-guided PRP or percutaneous tenotomy (Tenex) can help; cortisone injections are not indicated for this tendon.
Common symptoms
- Pain and tenderness just above the kneecap
- Pain when holding the leg straight
- Pain during squatting
- Pain going down stairs
What to expect at your visit
- 1.
A focused conversation
Dr. Gruner reviews your history, prior imaging, and goals — what you want to get back to doing.
- 2.
Point-of-care ultrasound
When useful, a diagnostic musculoskeletal ultrasound evaluates the injury in real time, with no radiation.
- 3.
A clear, individualized plan
You leave understanding the diagnosis, the non-surgical options, and the expected timeline — in plain language.
Rehabilitation protocol
What to expect week by week after your procedure. Your plan is individualized; follow these alongside your physical therapist.
Knee (Quad / Patellar Tendon) — Ultrasound-Guided PRP / Tenotomy Protocol
Week 0–1
Protect, reduce pain and swelling
- Non-weight-bearing with crutches ~4 days; knee immobilizer 1 week
- Begin gentle active knee ROM
- Gait training with crutches
Weeks 1–2
Restore ROM, progress weight bearing
- Continue knee ROM
- Begin core and lower-limb strengthening
- Upper-body aerobic/strength work; optional BFR
Weeks 2–4
Improve strength and tendon tolerance
- Begin isometric knee strengthening
- Joint mobilizations as needed
- Non-impact aerobic (bike); pool once incision healed
Weeks 4–6
Normalize gait, add balance
- Progress knee strengthening
- Initiate balance/proprioception
Weeks 6–8 (return to play)
Gradual return to sport
- No painful activities; no soreness > 24 hrs; no pain with running
- Gradual return to sport activities
Do not use NSAIDs (ibuprofen, Aleve, aspirin) for 4 weeks, and avoid ice for the first week — both blunt the healing response. Acetaminophen (Tylenol) is fine for discomfort. Care is tailored to you; use these guidelines with your physical therapist.
Frequently asked questions
- Should I get a cortisone shot for quad tendinopathy?
- No — cortisone is not indicated for the quadriceps tendon and can weaken it. Treatment focuses on progressive loading and physical therapy, with PRP or Tenex for resistant cases.